Chronic knee pain becomes a replacement question when it limits walking, stairs, sleep, work, or independence despite an appropriate course of treatment. By the end, you will know which symptoms warrant a surgical consultation, how doctors confirm the cause, and when replacement is premature or less suitable than another option.
Key takeaways
- Discuss replacement when pain limits walking, sleep, work, or personal care.
- Expect X-rays, an examination, and review of treatments before a recommendation.
- Consider surgery after appropriate non-surgical care no longer restores useful function.
- Match the operation to disease location, knee damage, age, and activity goals.
Which symptoms make a knee replacement consultation reasonable?
A knee replacement consultation becomes reasonable when chronic knee pain and stiffness persist despite treatment and substantially restrict walking, stair climbing, work, sleep, or ordinary self-care.
Stronger signals include pain at night and rest pain, repeated swelling, marked loss of motion, a bow-legged or knock-kneed change, or needing a stick, walker, or another person to remain independent.
| Finding | Why it matters | What to record |
|---|---|---|
| Pain despite treatment | Non-surgical care is not controlling symptoms | Which treatments helped and for how long |
| Reduced walking or stairs | Limited mobility is affecting daily function | Distance walked and number of stairs managed |
| Night or rest pain | Symptoms continue without activity | Whether pain wakes you or occurs while sitting |
| Deformity or stiffness | Alignment and movement may be deteriorating | Changes in knee shape and difficulty bending |
No single pain score, symptom duration, or minimum age automatically qualifies you. The key question is whether the knee has reduced your quality of life and whether non-surgical care has provided enough control.
An X-ray alone cannot answer that question. Some people have severe arthritis on X-ray with little pain, while others have significant symptoms with modest-looking changes. Doctors match your account of pain and function with an examination and standing weight-bearing X-rays.
Bring a record of your symptoms to the knee replacement consultation, rather than relying on the X-ray report alone. Include which activities you stopped, how long relief lasted after each treatment, and whether pain limits bathing, shopping, driving, or work.
What happens before a surgeon recommends replacement?
The decision begins with a history and physical examination, not an X-ray report. Severe pain can occur with modest X-ray changes, while marked arthritis can cause little pain, so symptoms, function, examination findings, and imaging must agree.
1. The clinician asks where the pain is, when it began, whether the knee locks or gives way, how it affects walking, stairs, sleep, work, and self-care, and what you have tried.
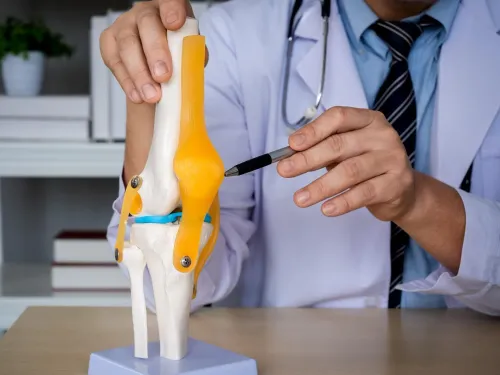
The examination assesses walking pattern, knee alignment, swelling, warmth, tenderness, ligament stability, range of motion, hip movement, and signs that pain comes from the spine.
2. Standing weight-bearing X-rays usually show joint-space loss, bone changes, knee alignment, and whether disease affects one compartment or several. Additional tests are chosen when the diagnosis is uncertain. Blood tests or joint-fluid analysis provide infection testing for knee pain when infection or inflammatory arthritis is suspected; hip or spine imaging can identify referred pain.
3. Give the clinician a complete treatment and health history. Include previous injections, physiotherapy, walking aids, prescribed medicines, reactions to treatment, diabetes, smoking, skin or dental infections, and other medical conditions.
This sequence stops a scan from driving the decision alone. It also identifies infection, inflammatory disease, referred pain, or another problem that needs treatment before an operation.
How do you know when non-surgical treatment has failed?
Non-surgical care has failed when a properly followed plan no longer gives useful relief, or relief does not last long enough for you to function. The decision depends on progress and daily ability, not simply on how painful exercise feels or what an X-ray shows.
- Complete a tailored plan that may include therapeutic exercise, physiotherapy for knee arthritis, education about pacing and load, activity modification, weight management when relevant, and a cane or walker.
- Review prescribed pain medicines with your clinician. Report stomach pain or bleeding, kidney problems, drowsiness, or other unwanted effects instead of silently stopping treatment.
- Treat rheumatoid arthritis or another inflammatory disease driving the knee symptoms. Uncontrolled inflammation can make replacement the wrong next step.
- Use injections only for selected short-term needs. A corticosteroid knee injection can reduce pain briefly, but injections do not repair cartilage; routine hyaluronan injections and arthroscopic washout are not reliable substitutes for replacement when end-stage symptoms persist.
- Judge exercise by gains in strength, movement, walking, and function. Initial soreness does not prove that physiotherapy has failed.
- Record whether pain still prevents work, shopping, bathing, driving, stairs, or sleep, and whether each treatment’s benefit repeatedly wears off.
Weight loss can improve pain and function when excess weight increases knee load, but you do not have to complete weight loss before referral. These details show whether continued conservative care remains worthwhile.
Which operation or alternative fits the pattern of knee disease?
The choice between partial versus total knee replacement, osteotomy, arthroscopy, and continued rehabilitation depends on disease location, ligament stability, alignment, remaining motion, and whether another treatment targets the real problem.
| Option | Pattern it fits | Main boundary |
|---|---|---|
| Partial knee replacement (unicompartmental knee replacement) | Arthritis mainly confined to one compartment; good ligaments, suitable alignment, adequate motion, and healthy remaining compartments | Unsuitable when arthritis is widespread or the knee is unstable, badly deformed, or very stiff |
| Total knee replacement | Arthritis affects several compartments, with major deformity, substantial stiffness, or damaged ligaments | It aims to reduce pain and improve walking, not create a normal-feeling knee or unlimited athletic capacity |
| Osteotomy for knee arthritis | A younger or active patient whose alignment overloads one side, with limited joint damage | It is not a general treatment for widespread arthritis |
| Knee arthroscopy | A repairable meniscal tear, loose body, or another specific mechanical problem | Knee arthroscopy indications do not include routine osteoarthritis alone |
| Continued rehabilitation | Pain remains manageable and walking, strength, or movement is improving | Reconsider the plan if function keeps declining despite a properly followed programme |
Replacement is premature when pain comes from the hip or spine, an isolated soft-tissue problem explains symptoms, X-rays show only mild disease, or infection and an uncontrolled medical condition remain untreated. Discuss recovery as well: swelling and weakness can last months, kneeling may stay uncomfortable, and high-impact sport is not the main goal.
What should you weigh before agreeing to knee replacement?
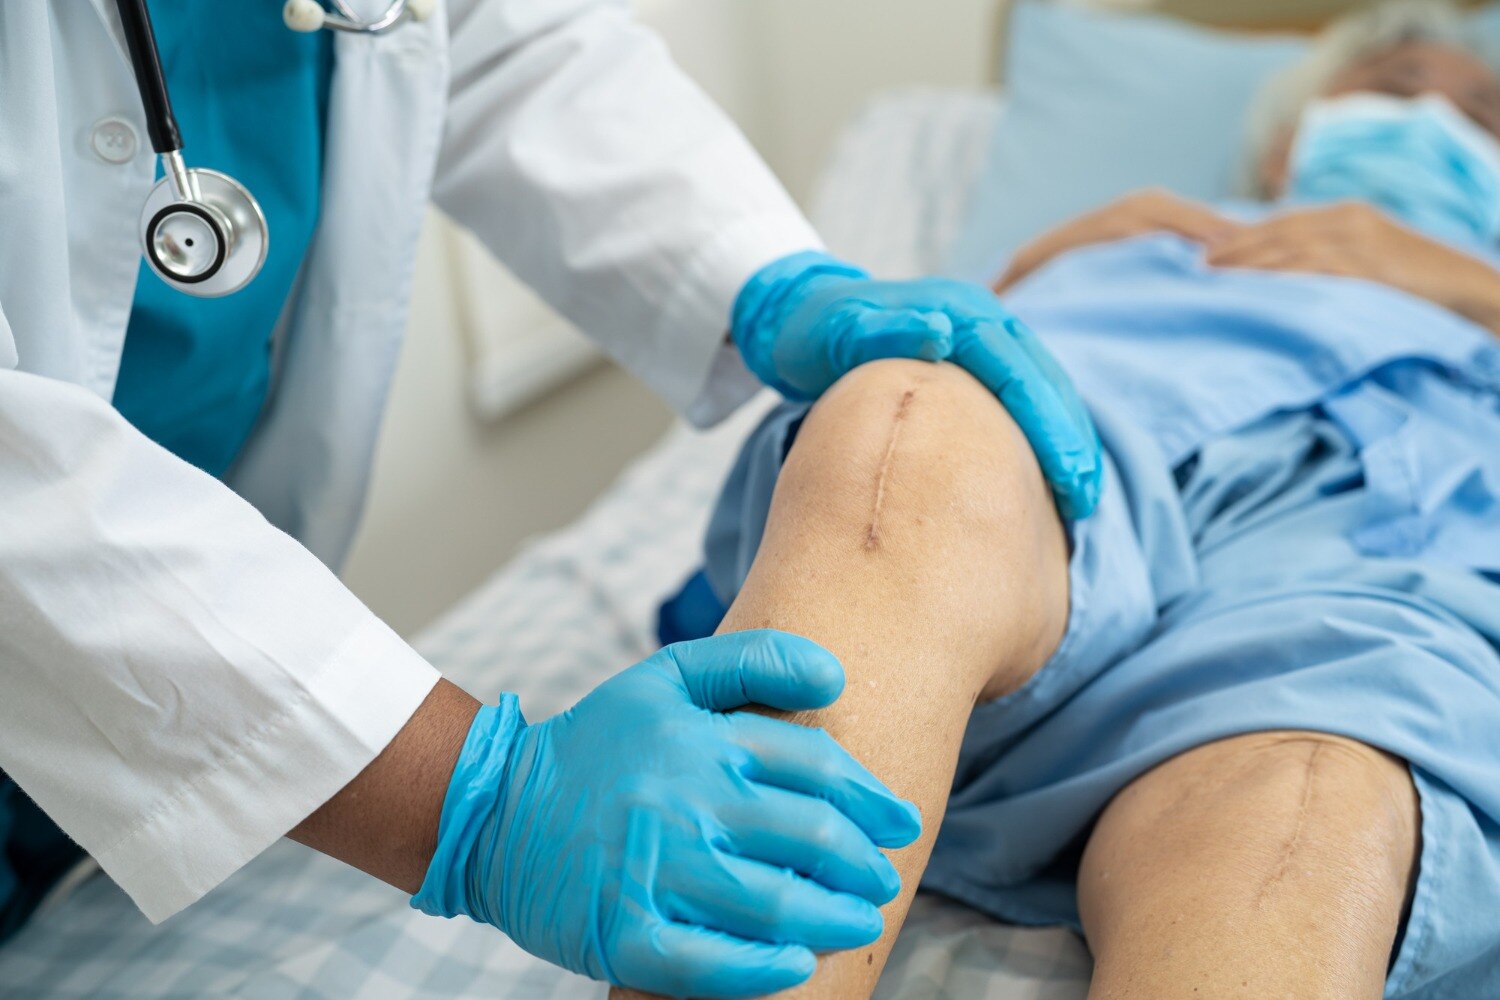
You and the surgeon should use shared decision-making to compare expected pain relief and mobility with the operation, knee replacement risks, and the knee replacement recovery timeline. The procedure resurfaces damaged joint surfaces with metal components and a plastic bearing; it does not promise a normal-feeling knee or unlimited activity.
| Consideration | What to expect | Question to discuss |
|---|---|---|
| Recovery | You are mobilized soon after surgery, but swelling, weakness, and stiffness can last weeks or months. Many people resume many normal activities around six weeks; full recovery can take up to a year. | Which activities matter most to you? |
| Complications | Infection, blood clots, nerve or blood-vessel injury, persistent pain or stiffness, instability, loosening, and wear can occur. Some problems require later revision surgery. | What is your individual risk? |
| Health preparation | Preoperative medical optimisation may include improving diabetes control, treating anaemia and active infections, addressing smoking, and managing obesity-related health problems. | Which risks need attention before surgery? |
| Eligibility | Age, sex, smoking status, or body mass index alone should not deny you an assessment. | What does your overall health and function indicate? |
A focused consultation at Dr. Manohar Rao Ortho can connect your pain diary, examination, standing X-rays, treatment response, and health risks to a choice between rehabilitation, a smaller procedure, partial replacement, or total replacement. Seek assessment when reduced mobility is changing your independence, not only when an X-ray report uses severe wording.
Related services
Knee Replacement also known as knee arthroplasty, is a transformative surgical procedure that relieves pain and restores function in severely damaged knee joints. View service → |
Primary Knee Replacement Primary Total Knee Replacement is the most common type of knee surgery performed by Dr. View service → |
Frequently asked questions
Which symptoms make a knee replacement consultation reasonable?
A consultation is reasonable when persistent knee pain and stiffness restrict walking, stairs, work, sleep, or ordinary self-care despite treatment.
What happens before a surgeon recommends knee replacement?
The surgeon reviews your symptoms and medical history, examines the knee, assesses function, and uses weight-bearing X-rays to evaluate joint damage.
How do you know when non-surgical treatment has failed?
Non-surgical care has failed when an appropriate treatment plan no longer provides enough pain relief or function for daily activities.
Which operation or alternative fits the pattern of knee disease?
The choice depends on whether damage affects one compartment or the whole knee, along with ligament stability, deformity, activity goals, and overall health.
What should you weigh before agreeing to knee replacement?
Weigh expected pain relief and mobility against recovery time, rehabilitation demands, surgical risks, implant longevity, and the limitations that may remain.
Related services
Complex Knee Replacement Complex or Revision Knee Replacement is performed in cases of failed previous surgeries, severe deformities, infections, or significant bone loss. View service → |
Total Joint Replacement **Total Joint Replacement Surgery by Dr. Manohar Rao H R** Dr. View service → |
Unicondylar Knee Replacement Unicondylar or Partial Knee Replacement is ideal for patients whose arthritis is confined to one compartment of the knee. Dr. View service → |